

The following is a guest post from my friend KingoftheCoast. He is a senior in college, studying economics. I cannot recommend his twitter more highly. I often learn about papers from him. I want him to become a professor — if you are a professor of economics reading this, I would give my strongest possible recommendation to admitting him to your program! You can subscribe to his blog here. Without further ado, here is the case against single-payer insurance.
Introduction
A common view on the left and center-left is that American healthcare is riddled with worthless administration. To be sure, there are occasional, internecine disagreements about the relative importance of administration versus “excessive” provider prices (ex: Levitz 2024, Smith 2024, Bruenig 2024) here, here, and here), but basically everyone agrees that the “do-nothing waste” can and should be eliminated with a government monopoly on basic health insurance – a single-payer system.
As someone with decent knowledge of both the American healthcare system and recent healthcare research, I think this is a terrible idea for about a thousand reasons. Demonizing administrative costs does not make much conceptual sense. A substantial portion of the purported costs to be saved would remain after a switch to single-payer. Once these are subtracted, the cost of having multiple administrative systems pales in comparison to the benefit to the consumer. Shifting to government run health insurance will be in no way more effective or efficient than our present system.
Sources of US Administrative Costs
In any system of health insurance, government monopoly or otherwise, there are certain administrative tasks that insurers need to perform. They must:
Design your plan, including premiums, out-of-pocket charges, approval processes, covered treatment classes, provider performance standards, provider payment models
Contract with providers to accept future patients
Sell the plan to consumers, and then upon the consumer falling ill
Review the providers’ payment request – sometimes prior to a treatment, but always after
In order to achieve all stages of this process (design, contracting, selling, review), resources must be used. Some people must design the plan, on computers the company will buy, in an office the company rents. This is something of a fixed cost, so each insurance company must have its own. UnitedHealth employs a different team of actuaries designing its plans than Kaiser Permanente does (“insurer admin costs”). And on the provider side, it takes more desk workers and physician time to manage compliance with a bunch of different payment contracts, than a single, universal one (“provider admin costs”). So if you set out with the goal of minimizing total admin costs – believing it is just “do-nothing waste” – you will indeed end up at the conclusion that a government monopoly is ideal, because a government monopoly takes the number of players and payment contracts to a minimum (one). To pundits like Matt Bruenig, Noah Smith, and Eric Levitz, this is where the analysis ends. The figure below summarizes their view quite well.

Source: Twitter
Bruneig, Smith, Levitz, and others are likely incorrect. There are three main reasons:
Much of the so-called higher admin costs are entirely fake
Much of the remainder directly save the system money
The higher admin costs unlock the far greater benefits of choice and competition
Fake Admin Costs
I am starting with the easiest one. In 2020, the CBO published a report that estimated the decline in administrative costs if the US were to transition to single-payer. Specifically, “single-payer” referred to Traditional Medicare – the government-run Medicare plan that currently enrolls about half of seniors – taking over as a basic insurance monopolist.
In that CBO report, they were nice enough to break down their guess-stimates by the source of the administrative cost savings. Here is what that figure looks like, using data from plans in the under-65, private market:
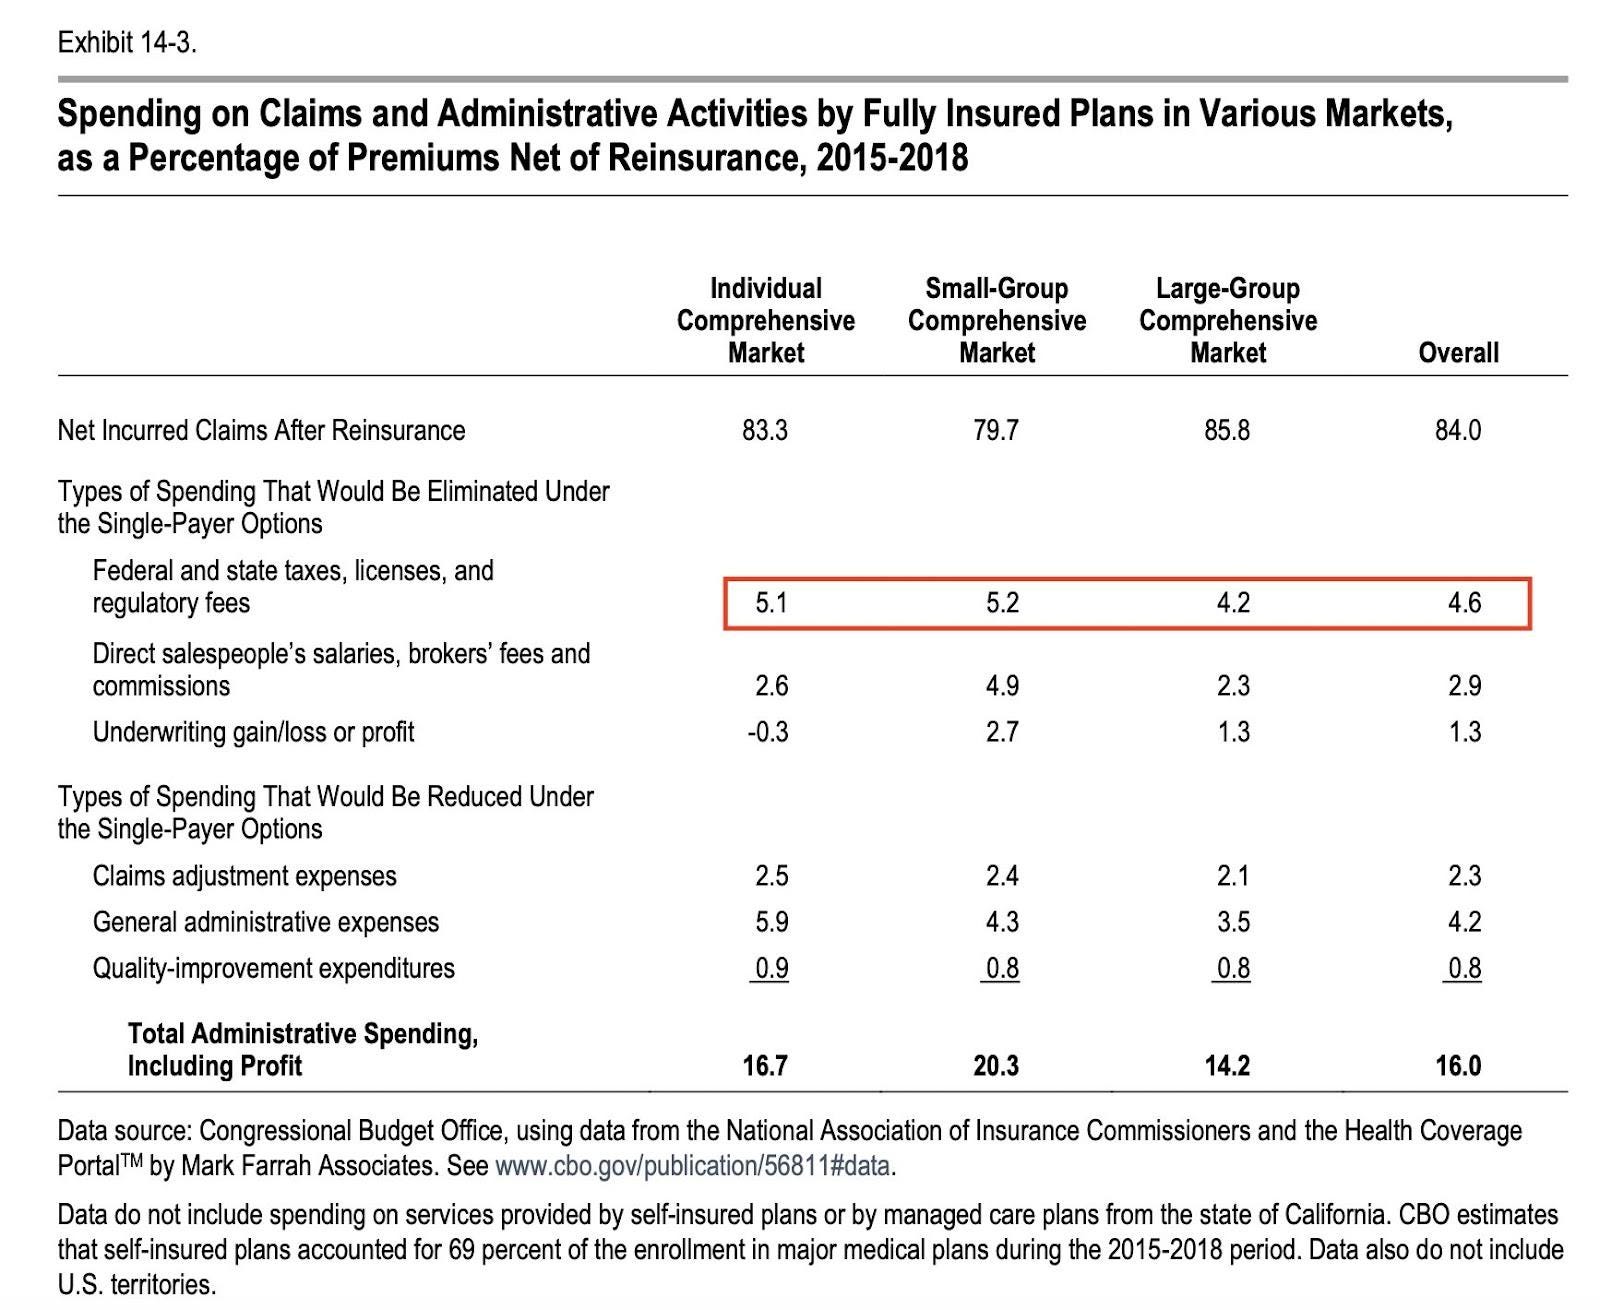
Source: CBO
Observe the red rectangle. It shows that of the 16% of premium revenue currently spent on administration by commercial plans, the single, largest category of “savings” is taxes and fees that Traditional Medicare is exempt from. In other words, at least 30% of the lower insurer admin costs under single-payer are due to an accounting gimmick. If there were a true level playing field between Traditional Medicare and private insurance plans, then the former would be required to pay the same taxes and fees, and consequently have much more comparable admin costs. If the government folded everything into one giant plan, it would forego the tax revenue. This doesn’t just go away! If we are cutting taxes on healthcare, something must fill the gap, be it spending cuts, tax hikes elsewhere, or a higher cost of debt. To include this as a cost saving is entirely specious.
Similarly, the portion of the administrative costs that is "underwriting gains/losses” cannot be properly counted as a saving to the public. While some commentators tout Traditional Medicare not trying to make any profit as a positive, this is ultimately an additional subsidy from the public. We the taxpayers are providing the government insurance plan with equity financing for free.
Unlike private health plans, which can and do lose money, there is no sense in which the administrators of Traditional Medicare are ever forced to “eat” an operating loss (see the Wall Street Journal). Instead, losses are just covered by the Treasury. So voters lose out in those bad states of the world, but are never compensated for it in good ones. The proper, positive cost of equity from the voters’ POV is hard to know, because it depends on their risk preferences. But I am pretty sure it is much higher than zero! So once again, we have an accounting gimmick that favors single-payer on grounds that have approximately nothing to do with actual efficiency.1 In any case, this category is chump change compared to the “taxes and fees” one, so I’m not going to dwell on it any further.
Admin that Directly Saves Money
Beyond the fact that a lot of the “higher” admin costs under the status quo are fake, it is still worth criticizing the view that higher administrative costs are, by definition, bad. This is not close to true, because many admin costs actively save the system money.
Let’s start with an obvious one: prior authorization. This is part of the “review” admin costs mentioned above, and it takes place prior to a treatment being given to a patient. The insurance administrators review medical information that lead the doctor to their prescription in order to gauge whether it meets their firm’s criteria for medical necessity. If it doesn’t, the administrators will refuse to cover the treatment and/or recommend a different one.2
Prior authorization is an important component of private insurers' higher admin costs, relative to Traditional Medicare, because Traditional Medicare does very little prior authorization – or care management in general. Exactly how important is unclear, so I won’t take a hard stand, but work from David Cutler suggests that it could represent a substantial portion of insurer and provider admin costs. (For those wondering, in the CBO graphic above, it is likely included in “claims adjustment expenses.”)
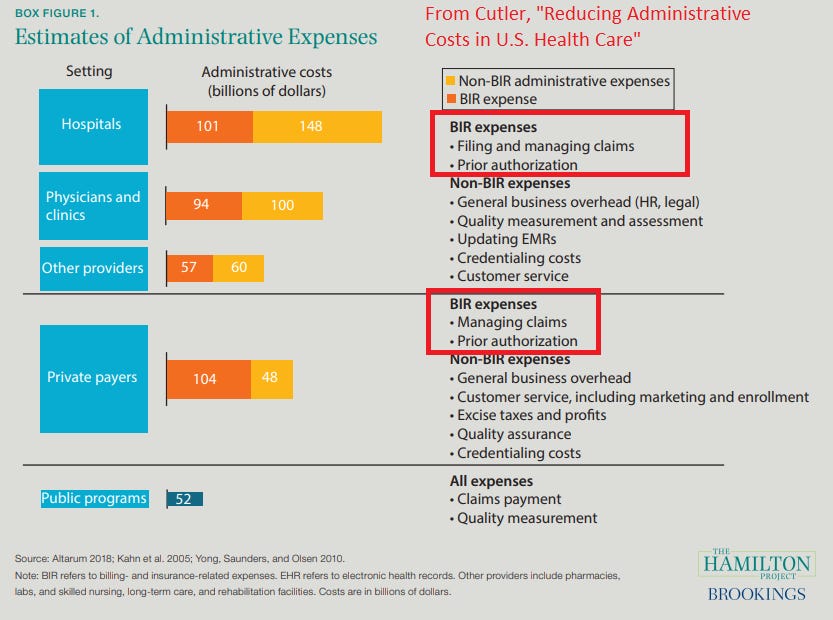
Source: Brookings
Despite its existence raising administrative costs, prior authorization still manages to save resources relative to a counterfactual without it. In fact, the strongest evidence to date finds that prior authorization yields large net savings (see here). To be specific, $96 lower healthcare spending for every $10 of admin costs (both insurer- and provider-side) that it generates. In the words of one of the authors, Zarek Brot-Goldberg: “This gives us a trade-off: Either we face wasteful health care spending, or costly administration.” Far from lowering the burden that insurance consumers or taxpayers face, eliminating many existing admin costs will exacerbate it by requiring those groups to finance more low-value, healthcare consumption.
Importantly, these findings on direct, net savings from higher admin costs are not limited to one study or the specific practice of prior authorization. Consider Jetson Leder-Luis and co. on the imposition of a prior authorization requirement by Traditional Medicare (see here). The requirement raised admin costs, but also massively reduced the use of unnecessary ambulance rides to dialysis clinics. This, again, generated huge net savings without measurably affecting patient health. Per the authors,
“Had the federal government required prior authorization throughout our sample period, it would have saved $4.8 billion and prevented 21.2 million unnecessary rides at an administrative cost of only $28 million per year.”
For admin costs other than prior authorization, consider Maggie Shi’s recent paper on the effectiveness of audits in Traditional Medicare (see here). Her work, similarly, points to net savings despite higher headline admin costs:
Every dollar Medicare spent on monitoring generated $24–$29 in government savings…I do not find evidence that the health of the marginal patient is harmed, indicating that monitoring primarily deters low-value care. Monitoring does increase provider administrative costs, but these costs are mostly incurred up-front and include investments in technology to assess the medical necessity of care.
Beyond how diligently insurers scrutinize claims before or after treatment (i.e. prior authorization and audits), let’s to the idea that private insurers may utilize more admin-intensive provider payment models. This too can generate net savings despite raising the admin burden. For a particularly vivid example, consider Blue Cross Blue Shield’s experiment with the "Alternative Quality Contract,” a pay for performance scheme that seems to have been effective at lowering medical spending and improving quality proxies (see Song et al. 2012).
I have been focusing on the administration of the insurance providers so far. People also make claims about the effect of single-payer on the administrative expenses of the healthcare providers by simplifying the billing procedures – or at least, they did. A recent paper by League and Shi has entirely settled things. Medicare used to have different firms handle the administration of Part A and Part B in a geographic area. After 2003, this changed to only a single firm for each. You can then infer the benefits of consolidating the billing system by using the staggered rollout of the system. They do indeed find that consolidating the system has fiscal benefits – 33 cents per admission! No, no, not 33 percent – 33 cents. Reining in America’s healthcare costs will not be achieved by rummaging through the couch for spare change.
Indirect Benefits of Admin: Choice and Competition
Not all of the cost-savings are due to entirely fake causes. There is a very real difference in administrative costs. UnitedHealth and Kaiser Permanente need to pay separate legal fees, separate IT teams, separate sales workers and actuaries. Roughly speaking, these costs are included in the above CBO figure as “Direct salespeople’s salaries, brokers’ fees and commissions” (3% of premium revenue) and “General administrative expenses” (4% of premium revenue).
Source: CBO
So if these extra admin costs are genuinely wasteful, that’s a clear argument in favor of single-payer, right? No. The problem with this line of argument is that it proves far, far too much. Duplication is just the “cost of admission” to get competition.
If your objective is to minimize these types of administrative costs in an industry, you will always conclude (no matter the characteristics of industry) that a government monopoly is superior to private competition. The government might as well monopolize the production of automobiles, offering just the F-150 to all, on the grounds that consumers won’t have to deal with pesky ads or sleazy dealers in their car search anymore. And even better, there will only be one IT department, one set of legal fees, and one design team. Every market for every good will be provided by the government alone. If you are thinking to yourself, “that is a completely one-sided characterization of the tradeoffs here,” then we are on the same page.
In reality, there are offsetting benefits of a non-monopoly system: consumer choice unlocks gains from variety, and competitive pressure feeds innovation.
The Benefits of Choice and Variety
Just as not everyone wants an F-150, not everyone wants the same health insurance plan. The most salient differences in preferences are going to be on coverage level, the degree of care management, and treatment breadth.
“Coverage level” is just the idea that some people prefer little financial risk (think, low out of pocket maximum) in exchange for higher premiums. Similarly, “degree of care management” is the idea that some people are fine facing more restricted access to care – a more narrow group of covered hospitals, more prior authorizations of prescription drugs, more primary-care gatekeeping of elective procedures – in exchange for lower out of pocket costs and/or premiums. This attribute of plans is best-displayed by the differences between Health Maintenance (HMO), Preferred Provider (PPO), and Fee-For-Service (FFS) organizations. Finally, “treatment breadth” the different preferences that people have over “basic” health insurance plans. People can buy more or less encompassing plans based on their preferences.
The idea that different preferences are quantitatively significant is not exactly a crank belief. Consider the following passage from “Let Them Have Choice”, by Dafny, Ho, and Varela:

Source: NBER
We can also infer the gains from having a variety of plans from works like Benjamin Vatter (2025). There, he focuses on the gains from the government changing how it discloses the quality of insurance plans; but such gains can come only is consumers have heterogenous preferences over the attributes of plans!
Objection 1: Imperfectly Rational Consumers
Nevertheless, I anticipate a number of objections. One that comes up a lot with left-wing healthcare wonks is the idea that health insurance consumers are not perfectly-rational.3 This is true in a sense; for example, many studies (see here) have found that consumers irrationally overweight plan premiums relative to deductibles. “Consumers do not always choose the very best plan available” is a very far cry, though, from “the benefits of consumer choice are insignificant.” The proper benchmark is a monopolistic, government-run system, not a perfectly competitive one. Research on whether consumer demand is sensitive to the most important things, such as premiums, cost-sharing, networks, and causal mortality, tends to be much more positive (ex: here, here, here). Moreover, to the extent that consumers would benefit from some help, nothing precludes policy measures that make it easier to compare plan options.4
Objection 2: Still Some Choice Under Single-Payer
A second objection is that single-payer does not eliminate all the benefits of choice, so my claim is overstated. For instance, many advocates – like Matt Yglesias – suggest that there will be a lively supplemental market, where people can purchase all the additional financial protection, treatment breadth, etc that their heart desires (see here). The main problem with this view is that private supplemental insurers will have worse incentives relative to integrated ones (see here). For instance, Amanda Starc has shown that integrated prescription drug plans (which cover both drugs and medical spending) offer much more generous coverage to their enrollees (see here). In line with the idea that insurers seek to internalize health externalities, this generosity is highest for drugs that combat chronic conditions and avoid costly hospitalizations. So I have a lot of trouble getting excited about access to a supplemental market under single-payer, given that it involves making these higher-quality options illegal!5
To sum up, while a certain class of higher admin costs are a legitimate downside of having consumer choice in health insurance, the benefits that come from letting people express their heterogeneous preferences should more than offset this. Just as not everyone wants an F-150, not everyone wants the same health insurance plan.
The Benefits of Competitive Pressure
But consumer choice is not just about unlocking gains from variety. Competition is also good, even when all consumers have very similar preferences, because it creates strong incentives to innovate.
Economics is littered with examples of competitive pressure facilitating technological progress – from FDA deregulation, to Chinese import competition, to the break-up of AT&T (see here, here, and here). Some popular theories to understand this phenomenon include…
Contestability: Firms have incentives to innovate when doing so meaningfully protects or expands their market share. Competitive pressure, by making market shares contestable, strengthens these incentives. (see here and here)
Bankruptcy Threats: Managers find it more costly to slack off, especially in hard to measure ways, when the threat of bankruptcy is higher. So competition reduces principal-agent problems and increases managerial effort. (see here)
Contracting Information: Managers find it more costly to slack off, especially in hard to measure ways, when their compensation is more closely linked to their effort. Competition in a market, by creating more natural comparators for relative performance contracts, reduces principal-agent problems and increases managerial effort. (see here)
As far as I can tell, the people who support single-payer do not generally disagree with these arguments in favor of competitive pressure; most of them are market socialists and center-lefties who concede that competition is generally important for productivity. What they seem to be implicitly saying is that competition is uniquely unimportant in health insurance.
I must dissent. Let’s focus on the most important margin for health insurers to innovate: care management.6 Obviously, innovation in this realm can involve delicate tradeoffs between 1) reducing wasteful healthcare spending 2) worsening health outcomes and 3) generating hassle costs. That’s why the north star of good health insurance is getting as much of “1)” as possible, and as little of “2)” and “3).” In my view, the highest-quality evidence suggests that competition is more capable of delivering on this promise than single-payer.
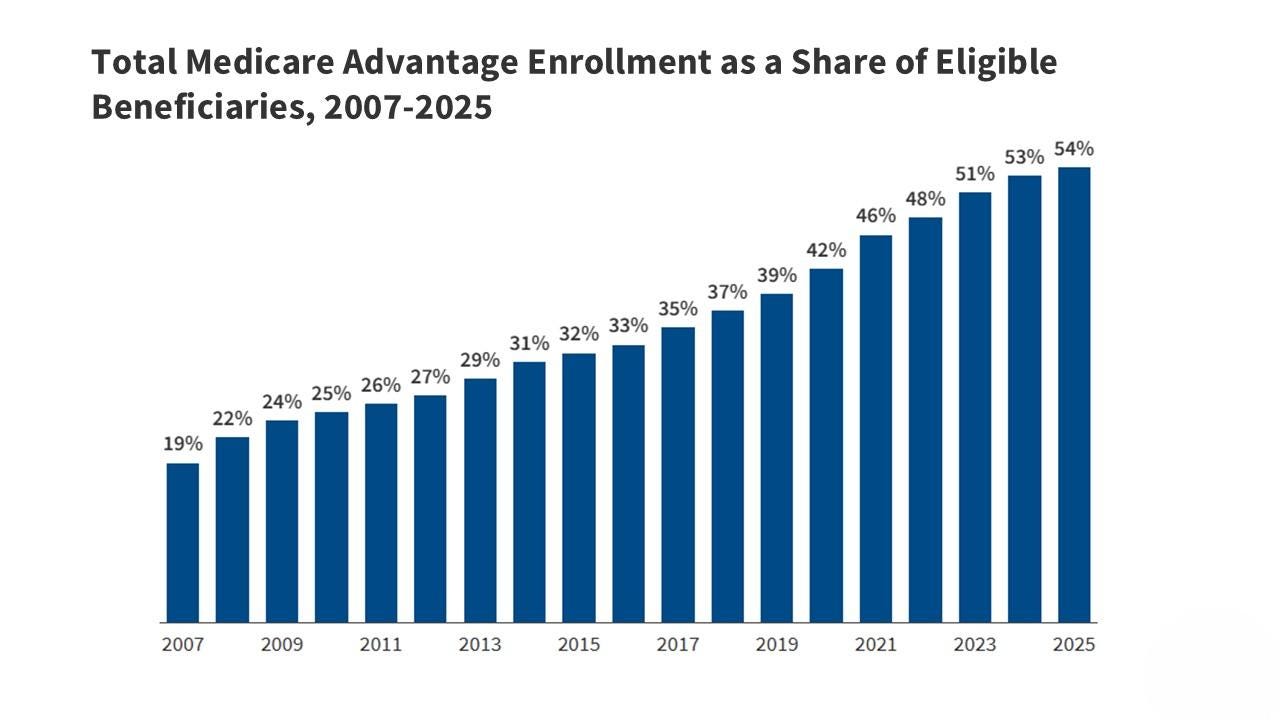
Source: KFF
A natural place to look is the Medicare program, which has both a public option (“Traditional Medicare”), and a market of private options (“Medicare Advantage” or “Medicare Part C”) each covering about half of eligible seniors. Given that Traditional Medicare is supposed to be the monopolist under single-payer, it makes sense to focus on its relative performance in this context. Another reason this setting is advantageous is because it isolates the effect of differences in care management, as opposed to prices paid to providers. For reasons that are not worth going into, both public Medicare and private Medicare plans end up paying about the same prices on average (see here).7 So how does Traditional Medicare perform relative to Medicare Advantage? In the words of practitioner Jason Abaluck, the literature here is, “many low-quality studies and a handful of very high-quality [ones].” For that reason, I am only going to focus on that best-identified group.
One classic article is, “The Consequences of Health Care Privatization: Evidence from Medicare Advantage Exits”, by Duggan, Gruber, and Vabson. The authors look at seniors who were forced out of the private market by plan terminations, in order to address selection bias. They find that exiting seniors experience huge and persistent increases in hospital utilization, despite measures of care quality – hospital ratings as well as rates of readmission, preventable hospitalization, survival – either declining or remaining unchanged. This combination of results, driven by private plans’ more selective coverage of hospitals and elective care, suggests that competition can fuel positive-sum innovation in care management.
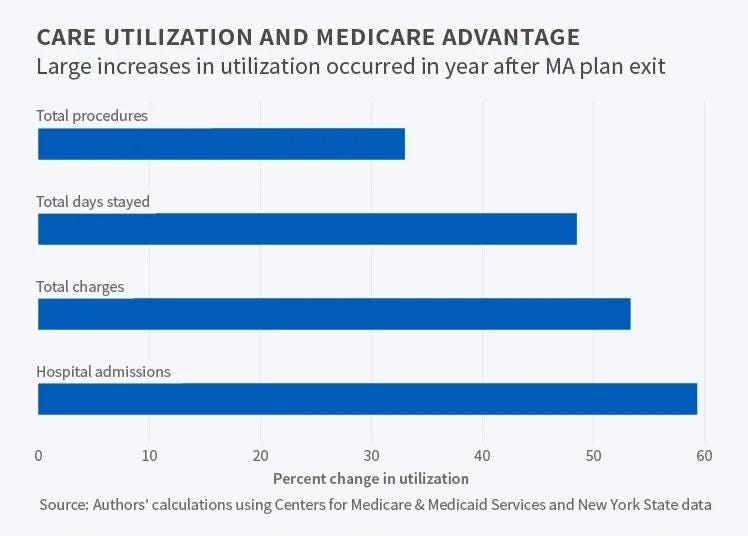
Source: NBER
Importantly, this positive result is replicated by an even better and more recent experiment on entry into the Medicare program. In a partnership with Inovalon, Harvard researchers were able to track and closely match individuals in the two years before they aged into either public or private Medicare, as well as the two years after. The (soon-to-be-published) paper confirmed that matched seniors joining Traditional Medicare utilized far more healthcare resources. This difference was mostly driven by more inpatient stays and emergency doctor visits, while utilization of primary/routine care and prescription drugs mostly remained unchanged. In line with the worry that this reflects lower-quality care management, the authors uncover much higher rates of avoidable hospitalizations, readmissions, and inappropriate medication use in the matched Traditional Medicare population. This again, illustrates that innovation by competing insurers can push us further in the direction of lower plan prices, without compromising plan quality.
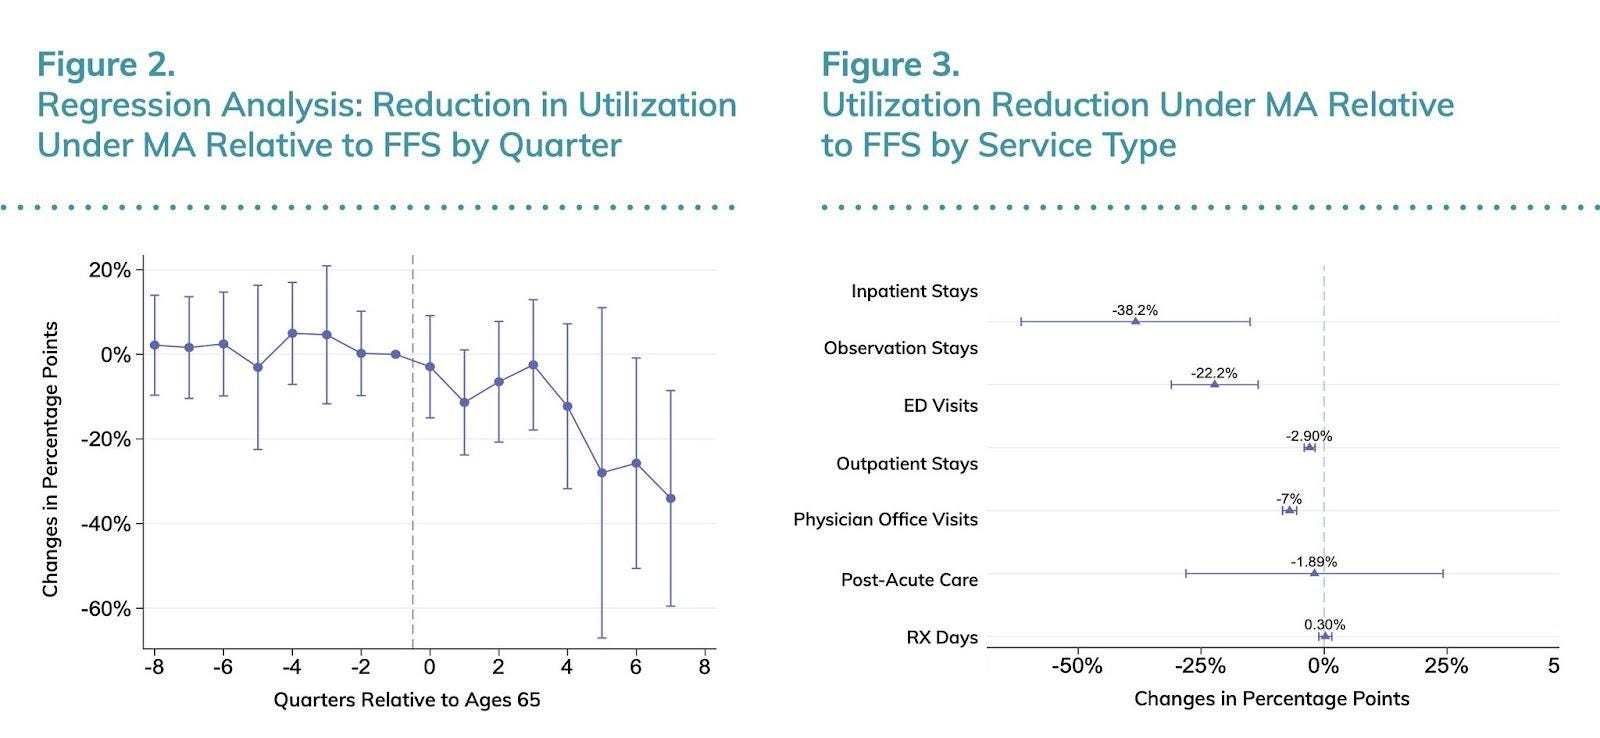
Source: Harvard-Inovalon Medicare Study
The innovations pioneered in the private Medicare market spillover to public Medicare. In “Medicare Payments and System-Level Healthcare Use”, Katherine Baicker and co. find that the greater entry of private Medicare into local areas changes market-wide treatment practices. In particular, they observe a large substitution of expensive inpatient care with cheaper outpatient care among Traditional Medicare patients, with little evidence of offsetting quality degradation. This is consistent with providers imperfectly differentiating their treatment styles based on the patients’ insurer, and again, suggests that competition can fuel innovation in care management. Medicare will also not reimburse you for procedures until the code associated with that procedure has been elevated to permanent. As per Dranove et al. (2022), this substantially slows down the adoption of new procedures. These changes are tested out first among private healthcare plans. Requiring everything to be approved in one big push by the monopoly provider is hardly likely to encourage innovation.
In summary, evidence from the Medicare Advantage program strongly suggests that, despite the claims of single-payer advocates, competition in health insurance is important.
Objection 1: Ignoring the Big Problem With Medicare Advantage
A smart skeptic will note that I am ignoring a key problem with Medicare Advantage, which is that the government chronically overpays private plans. Specifically, the government's goal is to pay plans a monthly lump-sum equal to what an enrollee would have cost (on average) to cover in traditional Medicare. However, because the government often has much worse information on the true health risk of enrollees, they are pretty bad at re-producing this counterfactual. This means that, despite private Medicare plans providing the traditional Medicare package at a lower cost and similar quality, taxpayers are not directly seeing the benefits. Instead, both the pure surplus (due to higher plan efficiency) and the zero-sum surplus (due to higher taxpayer subsidy) are solely going to Medicare Advantage consumers and plan sponsors – in the form of cheaper, more generous coverage and higher profits.8 In my view, a more reasonable world would be one where an enrollee's choice between a public option and a market of private options had no fiscal implications for the taxpayer.
Fortunately, there are feasible mechanisms that ensure this is always the case, while generating a tighter link between payments to all plans (public and private) and enrollee health risk. Below is one such scheme that I advocate for – which makes use of risk-based premiums and guaranteed issue – while ensuring that people with pre-existing conditions are protected.9 Ideally, this scheme would be universally applied, perhaps by lowering the Medicare eligibility age to 0. I strongly suspect that this will let us harness the aforementioned benefits of competitive pressure, without any of the overpayment side effects.
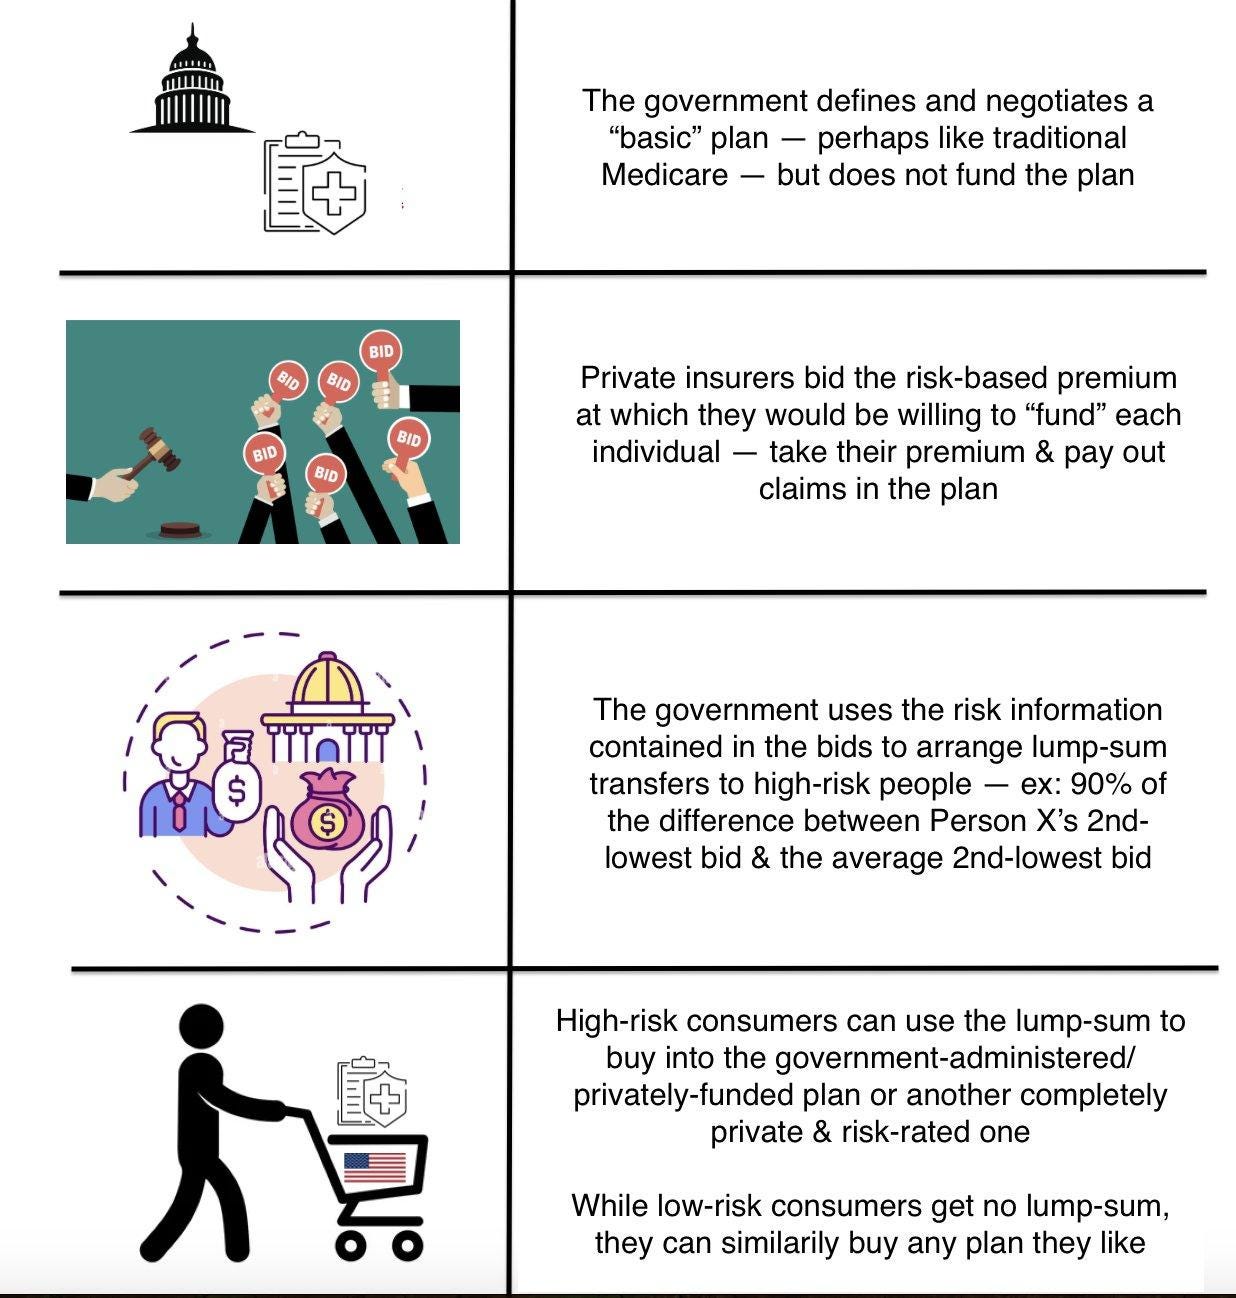
Source: Twitter
Objection 2: Is This Really the Effect of Market Competition?
Another objection to the evidence presented above is that it could just represent the effects of managed care, not competition per se. In other words, it shows that we should transition Traditional Medicare to a more HMO- or PPO-like plan design, not that we need a market for it. However, this perspective ignores a crucial fact: there is no universal effect of managed care plans. For instance, Jason Abaluck, Caceres Bravo, Hull, and Starc have convincingly shown that there exists large heterogeneity in the causal mortality effects of Medicare Advantage health plans. Thus there is no guarantee that Traditional Medicare would produce a managed care plan that is better than its current structure or the structure of its private peers. And, as argued at the outset of this section, that subpar result is more likely precisely because a monopolist faces weaker competitive pressure.
Objection 3: Political Competition Substitutes for Market Competition
A final, more theoretical objection is that I downplay the ability of political competition to substitute for market competition. While single-payer would not make use of competition between plans, there would still be electoral competition to modify the plan’s structure. Surely this pressure would push politicians to generate surplus for consumer-voters?
Ignoring how this directly contradicts the empirical evidence on Traditional Medicare v. Medicare Advantage, the theoretical issue here is one of degree. Yes, electoral pressure can also give politicians incentives to innovate. However, it is likely to be a much weaker motivator for suppliers than consumer choice. The reason is one of information acquisition. As a voter under monopoly, your incentives to become informed about better alternatives to your current insurance plan these alternatives are miniscule. The reason is simple: while you fully bear the costs of becoming an informed voter with certainty, the chances that your informed vote would ever be decisive in an election (i.e. deliver benefits to you) are on the order of 1 in 60 million. When voters are not willing to become informed about better alternatives and reward those proposing them, there ends up being little electoral incentive for politicians to seek them out in the first place. So innovation is slow. Contrast this with the incentives of consumers, whose probability of improving their situation, by becoming informed, is much closer to 100 percent. Remember Vatter? It is possible to raise consumer welfare by the equivalent of lowering your premiums by a third simply by providing more and better information about the quality of plans. This enhanced sensitivity to better alternatives, gives health insurance suppliers stronger incentives to seek them out – and, more broadly, points to the superiority of market competition over political competition.10 If you get rid of consumer choice, you get rid of all of this.
Conclusion
To reiterate, the key point in this piece is that high administrative costs in US healthcare are unlikely to represent “do-nothing waste.” Some of the purported costs are entirely fake. To include them in the possible savings of single payer shows either ignorance or dishonesty. Some of the costs are to prevent waste and fraud, which should be paid by Medicare now (although they are not). Of what is left, the cost of duplication pales in comparison to the plausible benefits of choice and competition in health insurance. When you put all of these together, the case for single-payer is nonexistent.
But what if I think the subsidy is a good thing? What if we want healthcare consumption to be cheap? Even if you believe that, there is no reason the subsidy can’t be delivered in a way that avoids favoritism – ex: an equal sized voucher that consumers can use at both government and private plans, as opposed to cheap equity only for the government plan.
Doctors are often in the business of prescribing a treatment and getting compensated for said treatment, through direct labor, referral fees, royalties, etc. Thus, they will have a financial incentive to prescribe excessively pricey and risky treatments. You need some way to check them, even when it does not rise to the level of outright fraud.
An even more forceful version of this argument would be that consumers are so irrational that the government is better off choosing for them. This paternalism argument is similarly straightforward to address. Since the government’s health insurance choices are ultimately disciplined by voters, any behavioral biases that lead to suboptimal consumer choices should also lead to suboptimal government choices. In fact, because people have stronger incentives to become informed about consumption choices than political choices, the behavioral biases should be worse under paternalism! (see Glaeser 2006)
An obviously good one is to group plans by “types” and standardize many aspects of plans within those groupings (see Ericson and Starc 2016). Another, more unconventional one, is making health insurance plans do all their cost-sharing through large copayments, as opposed to deductibles or coinsurance. The rationale for this is that most people don’t understand the latter two (see Loewenstein et al. 2013), and that they are bad ways to combat low-value consumption (see here).
A final objection is that choice in health insurance markets is bad, because it leads to adverse selection (ex: Kong et al. 2024, Marone and Sabety 2022). This objection is also dubious, but for reasons that I think are too complicated to explain in this (already long) piece – so look out for a follow-up. The short of it is that adverse selection, and its identified side effects, are trivial in a world where health insurers are allowed to charge premiums based on health risk (MR 2005). This is both eminently feasible to implement, and does not imply that people with pre-existing conditions will be screwed (see here). Nevertheless, even without risk-based premiums, I find it implausible that the welfare losses from adverse selection are so large as to nullify most benefits from choice. For instance, the evidence on reductions in insurer competition generally point to higher premiums and less generous plan offerings (see here).
Once again, this encompasses a lot of insurer decisions – their minimum performance standards for covered providers, their payment contracts with primary care “gatekeepers,” their use of prior authorization, their differential out-of-pocket charges across service types (ex: inpatient / outpatient), and so on.
This is directly in contrast to under-65 private plans (“commercial insurance”) which tends to pay significantly higher prices than Traditional Medicare. Why commercials generally pay higher rates is an interesting question, and one that I will explore in the future. While one view is that higher prices mostly represent wasteful provider rents (ex: due to anti-competitive hospital mergers), my view is that they more generally represent fair compensation for costly quality improvements. See here for a brief overview.
Some may argue that taxpayers get some surplus through spillovers that lower Traditional Medicare spending, which are large, but I am ignoring those for the sake of clarity here. In any case, I doubt they completely make up for the lower taxpayer surplus from overpayments.
Incidentally, this is the same scheme that should neutralize most of the adverse selection problems plaguing our status-quo, managed competition markets (see footnote 5)
There are other, complementary reasons to think that market competition, by allowing for consumer choice and multiple suppliers, actually improves peoples’ decisions as voters. For example, the greater information that consumers gather, can be used to inform future votes related to healthcare policy. Alternatively, having private options actually in the market would make it easier for voters to assess the relative performance of the government option. If this is the case, the strength of political competition would be downstream of the market competition.

Another important factor that I don't think I've ever seen discussed in this context is deadweight loss from taxation. The single-payer advocates aren't advocating funding this with a head tax or actuarially fair premium. They're advocating funding it with progressive income taxes, which means more deadweight loss from taxation. This is never counted as an administrative cost of single-payer health care.
The biggest challenge to reforming health care spending is that most people don’t see “pre-authorization limits low value procedures” and think “ah yes, resources being used more efficiently”. They think, “they are spending my money to deny me coverage!”